
To Buy Prograf Online Visit Our Pharmacy ↓

Why Prograf Blood Levels Matter for Safety
A single blood draw can feel like fate for someone recovering from transplant: clinicians chase a narrow window where the drug protects the graft without harming the patient. Regular measurements turn uncertainty into action, guiding timely changes so therapy stays effective.
Targeted tacrolimus levels reduce rejection risk while avoiding nephrotoxicity and neurotoxicity. Labs measure trough concentrations and trends; clinicians adjust dose based on numbers, timing, drug interactions, and clinical status. Patient adherence and communication ensure readings reflect true exposure, improving long-term outcomes. Tests inform safer, personalized care decisions, consistently monitored.
| Test | Purpose |
|---|---|
| Trough level | Assess efficacy/toxicity |
Types of Lab Tests to Monitor Prograf
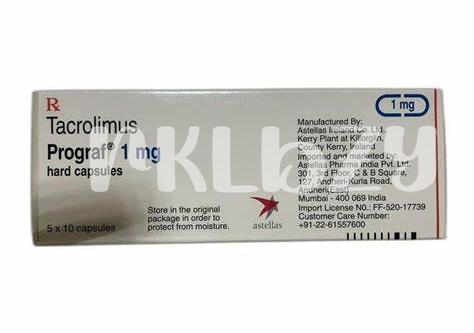
After transplant, routine blood draws become familiar checkpoints. Clinicians order trough level tests measured just before the next dose to assess immunosuppression intensity. These single point measurements are practical and guide immediate dose adjustments.
Some centers use abbreviated or full pharmacokinetic profiles, sampling at multiple times to estimate area under the curve (AUC). AUC gives a fuller picture of exposure and can reveal absorption issues or drug interactions missed by trough values.
Lab methods vary: immunoassays are common for speed, while mass spectrometry (LC-MS/MS) offers higher specificity and fewer cross reactions. Knowing which assay your lab uses helps interpret results and compare values across centers.
Beyond tacrolimus levels, labs check kidney function, electrolytes, and drug interaction screens; combining these results with clinical context keeps prograf therapy both effective and safe. Regular communication with transplant team enables timely dose adjustments routinely.
Interpreting Tacrolimus Results: Numbers That Count
A tacrolimus result is more than a number; it reflects dose, timing, absorption, and liver function.
Clinicians compare values to target ranges to balance rejection risk and toxicity—low values risk rejection, high values risk nephrotoxicity and neurotoxicity.
Lab timing matters: trough (pre-dose) levels are standard. Random or peak levels need careful context; always note time since last dose.
Modifiers like drug interactions, liver disease, and adherence alter prograf concentrations; discuss unexpected results promptly to guide safe dose changes. Follow-up testing confirms trends rather than single outliers for safer management decisions.
Target Ranges by Transplant Type and Timing
In the weeks after transplant, clinicians chase a narrow window to protect the new organ while avoiding toxicity. Trough concentrations are usually reported in ng/mL: for kidney recipients, early targets often hover around 8–12 ng/mL, later settling to 5–8 ng/mL; liver patients commonly aim for roughly 8–12 ng/mL initially and 5–8 ng/mL maintenance. Early targets generally apply to the first weeks to months after surgery, while maintenance ranges reflect long-term therapy.
Heart and lung recipients frequently require somewhat higher exposure—often 10–15 ng/mL early and 8–12 ng/mL once stable—while bone marrow or low‑risk patients may tolerate lower troughs. Individual factors, concurrent drugs and side effects mean prograf dosing is personalized, so periodic labs and close team communication guide safe adjustments. Dose adjustments also consider kidney function, infections, and drug interactions, and some centers use area-under-curve monitoring for finer control and outcomes.
Factors That Raise or Lower Prograf Levels
A sudden interaction can feel like a plot twist: foods, supplements, or new medicines may amplify or blunt prograf’s effect, changing how patients feel and lab numbers read.
Genetics, liver function, age, and adherence shape exposure; even grapefruit or certain antibiotics can push concentrations into risky territory, so clinicians watch levels closely.
Patients should tell teams about OTC drugs and herbs; simple timing changes around meals sometimes adjust absorption without flipping safety switches.
| Common Factor | Typical Effect |
|---|---|
| Grapefruit juice | Increases prograf levels |
| Rifampin antibiotic | Lowers prograf levels |
| Age | Alters metabolism |
Adjusting Doses Safely: When and How
Clinicians change tacrolimus dosing when levels drift from the target or when side effects emerge. Small, deliberate dose adjustments reduce swings; imagine nudging a dial, not flipping a switch, while monitoring labs and symptoms daily.
Dose changes are guided by trough concentrations taken before the next dose and by timing since transplant or infection. An abnormal value prompts review, not immediate overhaul; patterns over repeat tests drive confident, safer adjustments.
Typical changes are small—ten to thirty percent dose increases or decreases—tailored to severity. Account for formulation, adherence, drug interactions and hepatic function. After an adjustment, recheck troughs within three to seven days and repeat testing.
Hold or reduce doses when severe toxicity appears—rising creatinine, neurotoxicity, or infections—after consulting the transplant team. Never self-adjust; communicate medication changes, new drugs, or herbal use. Regular therapeutic monitoring prevents emergencies and ensures safer outcomes.
Before & After






Testimonials
Read out what our customers say about our services.
Read Testimonials



Join Our VIP List
Great News!
Comming soon our new location in Fort Worth (Alliance area)
3529 Heritage Trace Parkway, Suite 163
Fort Worth, TX 76244
Sign up now to join our VIP list and receive coupons