
To Buy Cephalexin Online Visit Our Pharmacy ↓

Cephalexin's Chemical Action on Bacterial Cell Walls
Imagine a locksmith jamming the bolts that hold a fortress together; the antibiotic slips into bacterial construction sites and blocks enzymes that stitch peptidoglycan strands. By preventing cross-linking of the cell wall it leaves the growing bacterium structurally weak, unable to resist internal pressure during division.
This focused attack targets penicillin-binding proteins that mediate peptidoglycan assembly, exploiting differences between bacterial and human cells. The result is rapid bactericidal activity while sparing host tissues, which explains why treatment works best during active cell growth and why dosing schedules encourage sustained exposure.
| Target | Effect |
|---|---|
| Penicillin-binding proteins | Inhibit cross-linking |
| Peptidoglycan | Wall weakening and lysis |
How It Targets Penicillin-binding Proteins Effectively
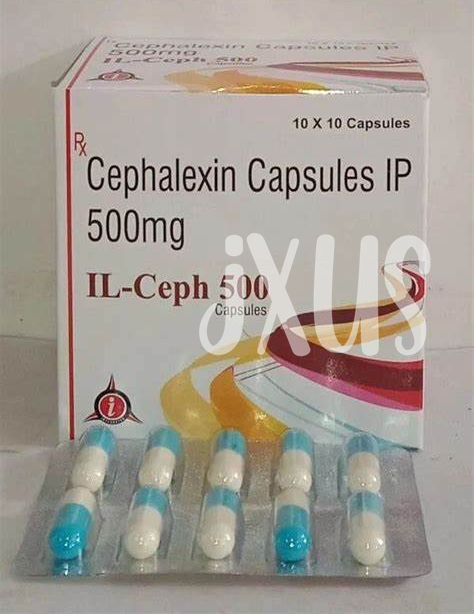
Imagine bacterial cell-wall construction as a team linking bricks; cephalexin arrives like a counterfeit brick that fits the lock of penicillin-binding proteins—enzymes (transpeptidases and carboxypeptidases) that make peptide cross-links. By acylating an active-site serine, the drug forms a stable acyl-enzyme complex that halts transpeptidation and leaves the peptidoglycan mesh unable to strengthen.
Left unreinforced, the wall succumbs to osmotic stress and bacterial autolysins, producing bactericidal lysis. Cephalexin’s scaffold gives it higher affinity for PBPs typical of Gram-positive cocci, which helps explain its clinical potency against staphylococci and streptococci, but different bacteria express varied PBPs so susceptibility depends on species-specific enzyme structures. Resistance factors, like altered PBPs or β-lactamases, can reduce cephalexin activity in many strains.
Bacterial Susceptibility: Which Bugs Cephalexin Kills
In everyday infections, cephalexin shines against many Gram-positive organisms, especially skin and soft tissue pathogens.
It reliably treats methicillin-sensitive Staphylococcus aureus and streptococci, and shows activity against common urinary Gram-negative rods such as Escherichia coli, Klebsiella, and Proteus.
Anaerobic coverage is limited, so deep abscesses or mixed anaerobic infections usually need alternative or additional agents.
Clinicians watch for resistant strains: methicillin-resistant S. aureus and certain beta-lactamase producers resist cephalexin, so culture results and local susceptibility guide therapy. Empiric choices reflect infection site, severity, and patient allergy history, plus comorbid conditions.
Absorption, Distribution, Metabolism, and Excretion Simplified

After oral intake, cephalexin is rapidly absorbed from the gut and reaches peak blood levels within an hour. Food may slow absorption but does not significantly reduce effect in practice.
It distributes into many tissues, skin, soft tissue and bone, with low plasma protein binding. The liver does little modification, so the active drug remains largely unchanged in systemic circulation.
Renal excretion clears most cephalexin, producing high urine concentrations helpful for urinary infections. Half-life is short, so dosing several times daily and renal adjustment are needed when kidney function falls.
Common Resistance Mechanisms Threatening Cephalexin's Effectiveness
Imagine a well-tuned lock and key: cephalexin fits bacterial wall-making machinery and jams it. Yet bacteria evolve tricks — enzymes like beta-lactamases cut the drug, altered penicillin-binding proteins lower binding, and reduced permeability or efflux pumps keep concentrations too low at their target. These adaptations can arise fast in communities under antibiotic pressure, so even familiar infections may become stubborn unless stewardship and rapid testing guide therapy and clinical vigilance.
A few classic culprits deserve attention: plasmid-mediated genes spread resistance between species, point mutations alter binding sites, and biofilm communities shield cells from concentrations effective in planktonic cultures. Clinicians therefore rely on culture, sensitivity testing, and local antibiograms to decide whether cephalexin will work. Preventing resistance means shorter, targeted courses, avoiding unnecessary prescriptions, and investing in infection control to stop those microscopic trades that permanently flip a cure into failure.
| Mechanism | Effect on Cephalexin |
|---|---|
| Beta-lactamase production | Inactivates the drug |
| PBP alteration | Reduces binding, lowers efficacy |
| Efflux/porin changes | Decreases intracellular concentration |
| Biofilm formation | Protects bacteria from exposure |
Practical Tips: Dosing, Interactions, Side Effects Overview
Begin with a clear dose plan: typical adult cephalexin is 250–500 mg every 6–12 hours, adjusted for infection severity and kidney function. Finish the full course even if you feel better. Missing doses lowers effectiveness and encourages resistance.
Watch interactions: antacids, iron, and metformin can alter absorption or effects; tell your clinician about other antibiotics or blood thinners. Common side effects are gastrointestinal upset, rash, and rarely allergic reactions; seek urgent care for hives, breathing difficulty, or severe diarrhea suggestive of C. difficile. Monitor kidney function and report unusual symptoms promptly.
Before & After






Testimonials
Read out what our customers say about our services.
Read Testimonials



Join Our VIP List
Great News!
Comming soon our new location in Fort Worth (Alliance area)
3529 Heritage Trace Parkway, Suite 163
Fort Worth, TX 76244
Sign up now to join our VIP list and receive coupons